Sildenafil vs Tadalafil vs Vardenafil for ED
Compare sildenafil, tadalafil, and vardenafil for ED. Review timing, food effects, side effects, and questions to ask before switching.

Sildenafil, tadalafil, and vardenafil all help improve erections with sexual stimulation. Tadalafil has the longest labeled window and a daily option. Sildenafil and vardenafil are usually taken about an hour before sex, and a high-fat meal can affect absorption. Your health history, medications, and preferences help determine which option fits.
How do PDE5 inhibitors help with erections?
During sexual stimulation, nitric oxide increases a messenger called cGMP, which relaxes smooth muscle and helps blood flow into the penis. Sildenafil, tadalafil, and vardenafil slow the breakdown of cGMP. They help the physical erection response, while low sexual desire deserves a separate discussion with your physician.
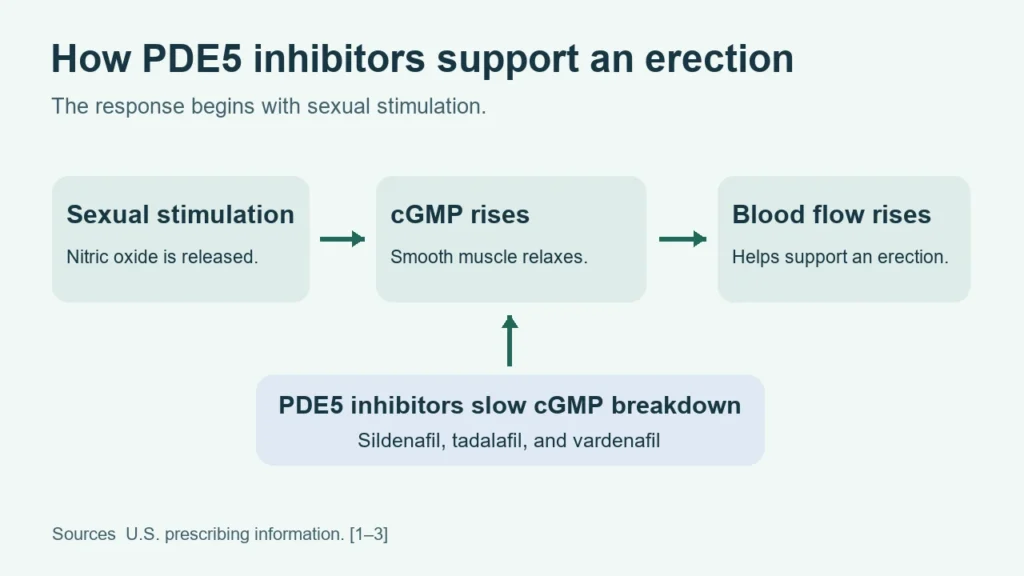
PDE5 occurs in other tissues, including vascular smooth muscle. That helps explain why these medicines can affect blood pressure and cause flushing or headache. Age-related vascular changes, diabetes, nerve problems, medications, and hormone changes can contribute to ED. Persistent ED can also be a marker of cardiovascular disease. [1–5]
Different doses reflect differences in each drug’s pharmacology. A milligram comparison or a laboratory potency ranking cannot tell you which will work better for you. Sexual stimulation remains necessary with all three. [1–4]
How do timing, duration, and food effects compare?
Tadalafil can improve erectile response up to 36 hours after an as-needed dose, and food has little effect on absorption. Sildenafil and vardenafil have shorter half-lives and are usually taken about an hour before sex. Peak blood levels, time to response, and how long the drug stays in the body are different measures.
| Medication | Usual labeled adult ED starting dose and timing | Peak blood level and terminal half-life | Food and practical considerations |
|---|---|---|---|
| Sildenafil (Viagra) | 50 mg as needed, usually about 1 hour before sex. Label allows 30 minutes to 4 hours before. | Peak 30–120 minutes when fasted, median 60 minutes. Half-life about 4 hours. | High-fat meals delayed peak by about 60 minutes and reduced peak concentration by 29%. [1] |
| Tadalafil (Cialis) | 10 mg as needed. For daily ED use, 2.5 mg once daily, with an increase to 5 mg when appropriate. | Peak 30 minutes to 6 hours, median 2 hours. Half-life 17.5 hours. | Take with or without food. As-needed benefit demonstrated up to 36 hours. [2] |
| Vardenafil (Levitra tablets) | 10 mg as needed, about 60 minutes before sex. | Peak 30–120 minutes when fasted, median 60 minutes. Half-life about 4–5 hours. | Can be taken with or without food. High-fat meals reduced peak concentration by 18–50% in food-effect studies. [3] |
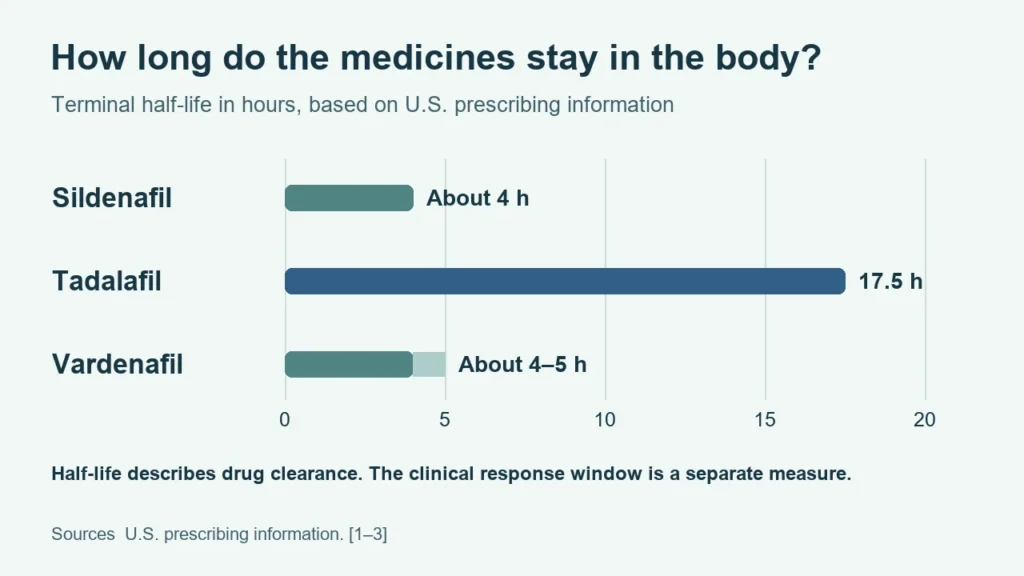
Sildenafil showed a diminished erectile response at four hours compared with two hours in one label study. With tadalafil, a 36-hour window does not mean a continuous erection, guaranteed response, or an entire weekend of coverage. As-needed dosing is generally limited to once daily, and certain conditions or medicines require lower doses or longer intervals. [1–3]
Which option fits your routine, and when should you switch?
A longer response window may suit a changing schedule, while a shorter-acting option can fit planned intimacy. Meal timing, side effects, price, and response can guide a switch. If the first prescription underperforms, ask your physician to review how you used it and to specify when a different medication can safely start.
- If timing varies, ask about as-needed or daily tadalafil. If you prefer planned use, discuss sildenafil or vardenafil and the timing of a high-fat meal. Side effects that occur with tadalafil may last longer because the drug clears more slowly. [1–3]
- If diabetes contributes to ED, discuss glucose and vascular health. Vardenafil has trial evidence in men with diabetes, as do other PDE5 inhibitors. The evidence does not establish vardenafil as the universal fastest or most effective option for diabetes. [1–4]
- If a medicine falls short, review timing, sexual stimulation, dose, food, alcohol, side effects, and underlying causes. The prescriber can adjust treatment or supervise a switch. Avoid overlapping PDE5 inhibitors. There is no universal switching interval, especially with daily tadalafil, kidney or liver impairment, or interacting medicines. [1–5]
- If paying cash, request the total cost for the exact strength and quantity, including consultations and follow-up. Compare FDA-approved generics and brand prices at the pharmacy. Coverage and cash prices vary. [6]
What side effects and interactions matter most?
Headache, flushing, nasal congestion, and indigestion can occur with all three medicines. Nitrates and guanylate cyclase stimulators such as riociguat are contraindicated. Your physician should assess whether sexual activity is medically advisable, review other drugs that lower blood pressure, and explain when symptoms such as sudden vision loss require urgent care.
Sildenafil can cause transient color vision changes, including a blue tint. Tadalafil can cause back pain or muscle aches. Heavy alcohol use can impair erections and increase dizziness or blood pressure drops, especially with tadalafil. Check with your clinician about alcohol in your situation. [1–4]
Tell your physician about chest pain, recent heart attack or stroke, arrhythmias, poorly controlled blood pressure, liver or kidney disease, inherited retinal disease, prior sudden vision loss, a curved penis, or conditions that predispose to priapism such as sickle cell disease, leukemia, or multiple myeloma. The restrictions vary by drug and diagnosis. Vardenafil has a specific QT warning for congenital long QT syndrome and certain antiarrhythmics. Alpha blockers and strong CYP3A4 inhibitors can require dose adjustments or avoiding a drug. [1–5]
Seek emergency care for an erection lasting more than four hours or chest pain during sexual activity. If you develop chest pain, tell emergency personnel which ED medication you took and when. Stop the medication and seek prompt medical care for sudden vision loss or sudden hearing decrease or loss. [1–3, 5]
Can these medications help with exercise, focus, or altitude?
Vascular effects do not establish better gym performance, faster recovery, or sharper focus in healthy adults. Tadalafil has a separate indication for pulmonary arterial hypertension, where it can improve exercise ability. Travel medicine guidance discusses it for prevention of high-altitude pulmonary edema in selected susceptible travelers. Neither application establishes a benefit for healthy athletes or routine acclimatization. [7, 8]
Common questions about PEPLIX HEALTH
Peplix Health is a cash-pay telehealth service managed by Monarch Brands LLC. An independent, board-certified physician reviews your symptoms, cardiovascular history, and medications before choosing a treatment or individualized dose. When an eligible compounded medication is appropriate, a state-licensed pharmacy can fill a patient-specific prescription subject to Section 503A and applicable state requirements.
Can I combine tadalafil with sildenafil or vardenafil?
The prescribing labels advise against combining PDE5 inhibitors. Overlap can lower blood pressure and increase side effects. Ask your prescriber about a clear switching plan if you need a different timing window. A specialist can review limited evidence for selected refractory cases. [1–3, 11]
Can I cut a tablet to adjust my dose?
Ask your pharmacist about your exact product. Cialis labeling specifies taking the tablet whole. For other products, follow their specific labeling and your pharmacist’s guidance, since score lines and split-dose evaluation vary. [2, 9]
What if the medicine stops working or never works for me?
If the effect changes over time, ask for a review before assuming tolerance or increasing the dose. Diabetes, vascular disease, neurological conditions, psychological factors, and testosterone deficiency can affect erections. A clinician may check morning total testosterone and discuss a vacuum device, alprostadil, or urology referral. [4, 5]
What if my main concern is low desire?
Tell your physician directly. Low desire can have hormonal, psychological, relationship, or medication-related causes. Bremelanotide (PT-141) acts at melanocortin receptors and is FDA-approved for certain premenopausal women with acquired, generalized low desire. It is not indicated for men, and evidence does not support routine combination with ED drugs. [4, 10]
Do supplements or 503A compounding change my options?
Evidence for L-arginine and ginseng suggests at most small erectile-function effects in selected patients. Evidence for L-citrulline is limited. FDA-approved products are available through licensed pharmacies. A 503A drug is compounded for an individual patient under applicable requirements, and compounded drugs do not undergo FDA premarket review for safety, effectiveness, or quality. [11–13]
For consultation information, see our low testosterone guide or start an online assessment.
Sources
- FDA. Viagra prescribing information.
- Eli Lilly. Cialis U.S. prescribing information.
- FDA. Levitra prescribing information.
- American Urological Association. Erectile dysfunction guideline.
- Princeton IV consensus. PDE5 inhibitors and cardiac health.
- FDA. Generic drugs questions and answers.
- DailyMed. Adcirca tadalafil label for pulmonary arterial hypertension.
- CDC Yellow Book. High-altitude travel and altitude illness.
- FDA. Tablet splitting.
- FDA. Vyleesi bremelanotide label.
- European Association of Urology. Management of erectile dysfunction.
- FDA. Federal provisions for human drug compounding.
- FDA. Compounding questions and answers.
This article is for general education and is not medical advice. Talk with a licensed clinician before starting, stopping or changing any treatment. Compounded medications are not FDA-approved. See our safety information.
Keep reading

Testosterone
What Is Enclomiphene and How Does It Compare With TRT?
Compare enclomiphene, TRT, and Clomid for low testosterone. Learn what trials found about sperm counts, side effects, and FDA approval.

Testosterone
Does Enclomiphene Build Muscle?
Does enclomiphene build muscle? Review the evidence on testosterone, lean mass, fertility, and what to discuss before treatment.

Testosterone
MCT Oil vs. Seed Oils in Injectable Testosterone
Compare MCT, sesame, and cottonseed oil in injectable testosterone. Learn what carriers do and what to ask about irritation or allergies.