What Is Native Testosterone and How Does It Differ From TRT Esters?
Learn how testosterone base differs from TRT esters, what oral studies found, and what to ask about fertility, monitoring, and compounding.

Native testosterone, also called testosterone base, is the same molecule the body produces, without an attached ester. A small study showed that a specific oral formulation could raise testosterone into a physiological range. Evidence remains limited on long-term symptom relief, safety, and fertility compared with established testosterone replacement therapy options.
What does testosterone base mean?
Testosterone base is unesterified testosterone. An ester is a chemical group attached to testosterone to change how a formulation is absorbed or released. Once the ester is removed in the body, it releases active testosterone. The route, formulation, and delivery vehicle all influence how long blood levels stay elevated.
Testosterone was isolated and named in 1935. Today, the term “native” describes the hormone’s chemical structure. It gives no information about how a product was manufactured, its purity, or how it will behave after swallowing. Oral testosterone base can be broken down extensively in the gut and liver before it reaches circulation. A lipid-based vehicle can change absorption, in part by promoting uptake through the lymphatic system. [1,2]
| Formulation or route | How it delivers testosterone | What to discuss with a physician |
|---|---|---|
| Oral testosterone base | Uses unesterified testosterone. Absorption, peaks, and food effects depend on the formulation. | What evidence supports this exact formulation, and when should labs be drawn? |
| Testosterone cypionate, enanthate, or propionate | Injectable esters can slow release from the injection site. Propionate is shorter acting than cypionate and enanthate. | What are the product’s approval status, dose interval, and expected peaks and troughs? |
| Testosterone undecanoate | An ester available in oral and long-acting injectable formulations. These routes have different absorption profiles and monitoring requirements. | What does the exact product label say about meals, monitoring, or office administration? |
| Transdermal testosterone | Many gels deliver testosterone base through the skin. FDA-approved options exist. | How should you limit skin transfer and monitor blood levels? |
Half-life is the time it takes for the measured drug concentration to fall by half during elimination. An injected ester can extend apparent half-life by slowing release. Intramuscular cypionate, for example, has an approximate half-life of eight days in its labeling. A shorter exposure can create a different peak-and-trough pattern, but restoring a natural daily rhythm or preventing suppression requires separate evidence. [1–4]
What does research show about oral native testosterone?
A small 2021 study found that one lipid-based oral testosterone base formulation raised blood testosterone into a physiological range and produced a lower DHT-to-testosterone exposure ratio than the oral ester tested. These findings describe how those products behaved over hours. Longer comparative trials would be needed to establish symptom and safety differences.
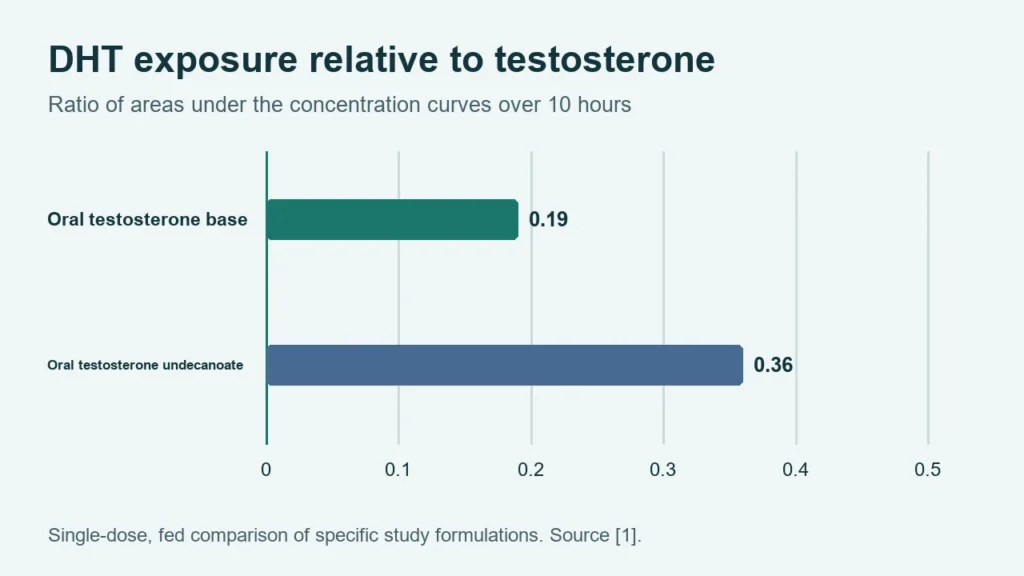
Dihydrotestosterone (DHT) is made from testosterone by 5-alpha reductase. After single doses taken with food, mean testosterone peaked at 1.4 hours with the native formulation and 4.2 hours with oral undecanoate. The DHT-to-testosterone exposure ratio over 10 hours was 0.19 and 0.36, respectively. Exposure was measured by the area under the concentration curve. These findings are specific to the formulations tested. DHT plays a role in androgenetic hair loss in susceptible people, and the study did not assess hair loss, blood pressure, or cardiovascular events. [1,2,5]
Testosterone replacement for documented hypogonadism can improve libido and some aspects of sexual function and increase lean mass. Effects on erections, strength, physical performance, mood, and energy vary. Evidence for improved memory or concentration is limited. The short oral study cannot establish those benefits for testosterone base or show that it is less suppressive, safer for the kidneys, or associated with fewer adverse effects. FDA updated testosterone labeling in 2025 to reflect cardiovascular trial findings and blood pressure increases. [4,6]
Does adding enclomiphene protect fertility on TRT?
External testosterone can reduce signals from the brain and pituitary to the testes and lower sperm production. Enclomiphene by itself has been studied in selected men with secondary hypogonadism. Evidence for combining it with oral testosterone base is limited. Normal LH and FSH levels alone cannot show that sperm production is preserved.
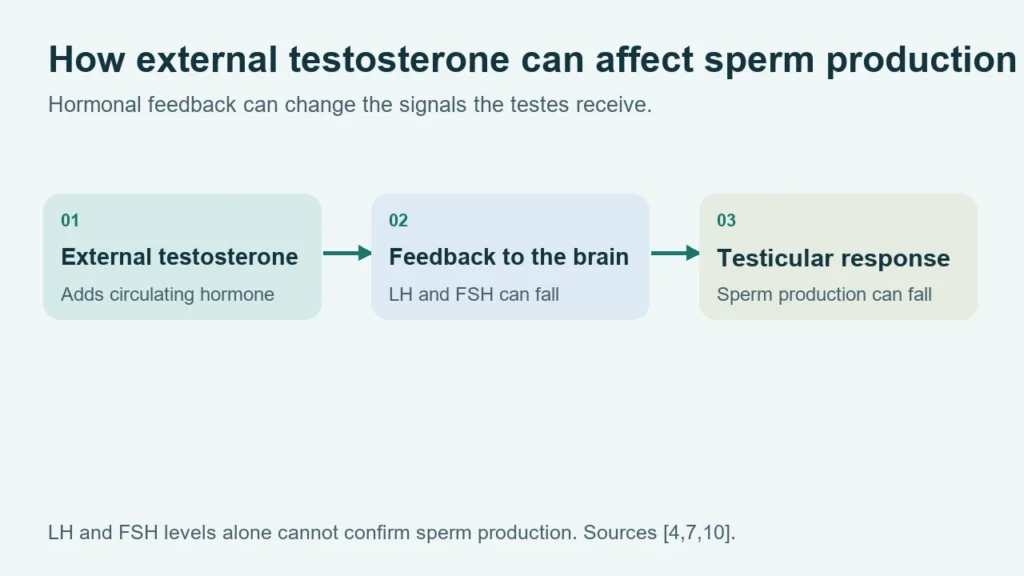
Enclomiphene is a selective estrogen receptor modulator. By reducing estrogen feedback at the hypothalamus and pituitary, it can increase luteinizing hormone (LH) and follicle-stimulating hormone (FSH). These hormones support testicular testosterone production and sperm development. A trial of enclomiphene alone reported preservation of sperm counts over the study period in selected men with secondary hypogonadism. This drug lacks FDA approval. [7,8]
A company-authored white paper from Maximus reported about fourfold higher total testosterone and fivefold higher free testosterone under its optimized combination conditions, with levels exceeding the 99th percentile in that analysis. It also reported LH and FSH within the lab’s reference ranges, lower estradiol within range, and self-reported changes in energy, strength or endurance, work performance, and quality of life. The report did not establish preserved fertility, fewer cases of breast enlargement or fluid retention, or prevention of mood changes. Elevated levels are a finding from that analysis. The treatment goal in clinical guidelines is generally a mid-normal range. [4,9]
Pregnenolone is a precursor in steroid hormone synthesis. The evidence cited here does not establish whether adding pregnenolone to this combination improves energy or mood. Discuss your fertility plans before starting external testosterone and ask whether a semen analysis or a reproductive urology referral is appropriate. [4,9,10]
What should a clinician check before prescribing testosterone?
A licensed clinician evaluates symptoms, confirms low testosterone with repeat morning blood tests, and looks for the cause. Free testosterone can help when total levels are borderline or binding proteins may affect interpretation. If treatment is appropriate, the clinician selects a formulation, individualizes the dose, and sets a follow-up plan.
- Confirm the diagnosis. Low libido, erectile difficulties, fatigue, and changes in body composition can have several causes. The Endocrine Society recommends two separate fasting morning total testosterone tests and free testosterone when indicated. LH and FSH help distinguish testicular causes from pituitary or hypothalamic causes. [4]
- Review risks and goals. Discuss fertility, blood pressure, hematocrit, relevant prostate screening, sleep apnea, and other conditions. Guidelines recommend against starting testosterone in people planning fertility in the near term. [4,6]
- Plan monitoring before the first prescription. Ask when to draw follow-up blood work for the chosen formulation and how results, symptoms, and adverse effects will guide dose changes. [4]
Common questions about PEPLIX HEALTH
Independent, board-certified physicians evaluate symptoms, lab results, and treatment goals. Monarch Brands LLC provides management services for Peplix Health. During a cash-pay visit, ask which options are clinically appropriate, whether they are available in your state, and what the prescription, blood work, and follow-up would cost before you make a decision.
Is oral testosterone base the same as FDA-approved oral testosterone?
FDA-approved oral products such as Jatenzo and Kyzatrex contain testosterone undecanoate. Ask your physician for the exact product name, active ingredient, and approval status. A compounded oral testosterone base product lacks FDA approval. [11,12]
Who fills a prescription when compounding is appropriate?
When an individual patient need warrants compounding and applicable requirements are met, a state-licensed pharmacy operating under Section 503A can prepare a patient-specific prescription. Ask which pharmacy will dispense it and what monitoring your prescriber recommends. [12]
For consultation information, see our low testosterone guide or start an online assessment.
Sources
- Newell-Price et al. – oral lipidic native testosterone pharmacokinetics
- Review – testosterone replacement formulations
- FDA – testosterone cypionate prescribing information
- Endocrine Society – male hypogonadism clinical practice guideline
- FDA – DHT and androgenetic hair loss mechanism
- FDA – 2025 testosterone labeling changes
- Kim et al. – enclomiphene monotherapy and sperm counts
- FDA – enclomiphene application history
- Maximus – company-authored combination protocol white paper
- NCBI Bookshelf – steroid hormone synthesis
- FDA – oral testosterone undecanoate labeling records
- FDA – Section 503A compounding requirements
This article is for general education and is not medical advice. Talk with a licensed clinician before starting, stopping or changing any treatment. Compounded medications are not FDA-approved. See our safety information.
Keep reading

Testosterone
What Is Enclomiphene and How Does It Compare With TRT?
Compare enclomiphene, TRT, and Clomid for low testosterone. Learn what trials found about sperm counts, side effects, and FDA approval.

Testosterone
Does Enclomiphene Build Muscle?
Does enclomiphene build muscle? Review the evidence on testosterone, lean mass, fertility, and what to discuss before treatment.

Testosterone
MCT Oil vs. Seed Oils in Injectable Testosterone
Compare MCT, sesame, and cottonseed oil in injectable testosterone. Learn what carriers do and what to ask about irritation or allergies.